Heart Transplant Waitlist Could Be Reordered by New Risk Score
How AMUS Could Change the Allocation Landscape
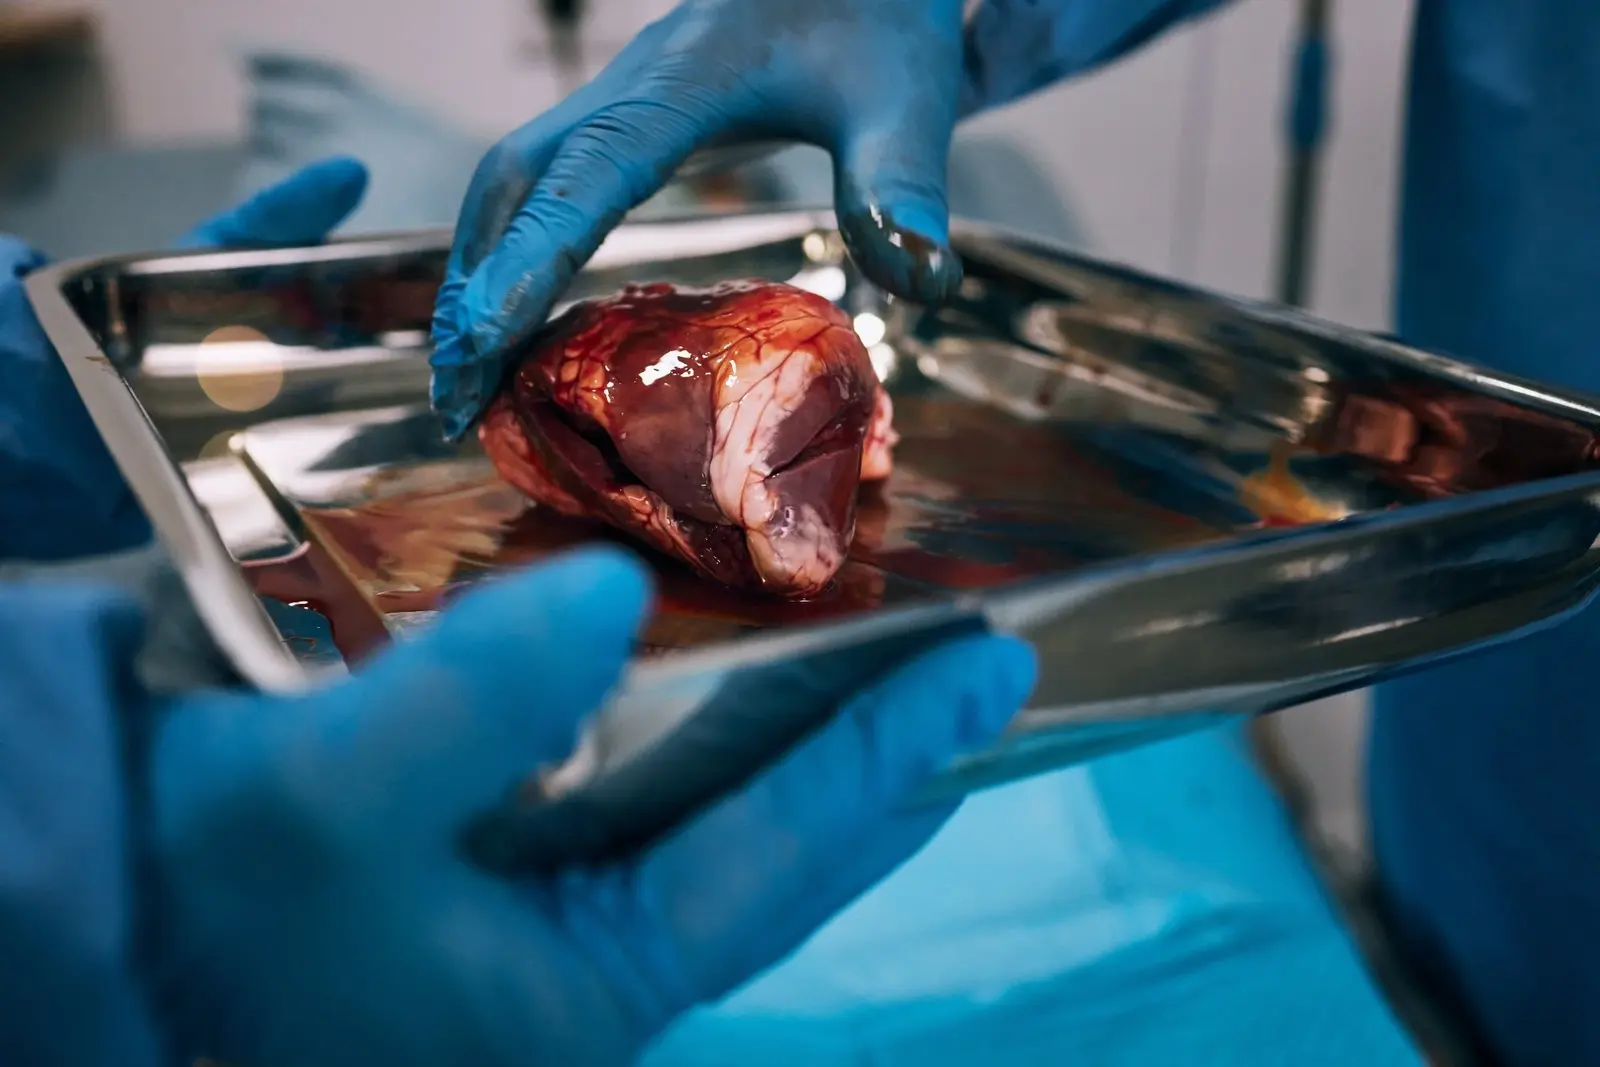
A team of researchers examined data from over 33,000 heart‑transplant candidates in the United States and found that a simple mortality risk score outperformed the current six‑tier system used to prioritize patients. The study, published in the American Journal of Transplantation , suggests that the new score could save lives by ensuring the sickest patients receive organs sooner and by limiting manipulation of the listing process.
Health news
 Exercise and Mood: Italian Study Links Physical Activity to Lower Depression Symptoms
 Screen Time in Childhood Linked to Unexpected Cognitive Boost in Teens, 8‑Year Study Shows
 Workplace stress and anxiety are taking a heavy toll on employees, with one in three workers reporting that the strain is not easing
 Daily Food Habit Tied to Lower Risk of Anxiety and Depression
The current system assigns patients a status from one to six based on a mix of clinical factors and physician judgment. However, the new score, called the Adult Medical Urgency Score (AMUS), relies on objective variables such as blood pressure, oxygen levels, and laboratory results. In head‑to‑head comparisons, AMUS correctly predicted 80 % of deaths on the waiting list, whereas the existing system achieved only 68 %. The researchers argue that the higher accuracy would reduce the number of patients who die while waiting and make organ allocation more transparent.
Can the Score Prevent Gaming of the System?
The AMUS model was built using a training cohort of 20,000 patients and then validated on a separate group of 13,000. It assigns a numerical risk score to each candidate, with higher values indicating a greater likelihood of death. Because the score is derived from routinely collected data, it can be updated in real time as a patient’s condition changes. The study’s authors note that the system would be easy to integrate into existing transplant registries and would not require additional tests or specialist input.
Dr. Emily Hart, a transplant cardiologist not involved in the study, said the new approach could „streamline decision‑making and reduce the subjective element that sometimes leads to inequities.” She added that the score could help transplant centers identify patients who might benefit from earlier intervention, potentially lowering the need for emergency surgeries.
What Happens Next for the Transplant Community?
One concern with any ranking system is that patients or providers might try to manipulate the criteria to gain priority. The AMUS score’s reliance on objective, hard‑to‑falsify data reduces this risk. In simulations, the researchers found that attempts to artificially inflate a patient’s status had minimal impact on the overall ranking. The authors suggest that regulators could adopt the score as a mandatory component of the allocation algorithm, thereby standardizing practice across all centers.
The study also explored how the score would affect organ utilization. By prioritizing patients with the highest mortality risk, the model could increase the number of transplants performed in the critical window before a patient’s condition deteriorates. This, in turn, could improve post‑transplant survival rates and reduce long‑term complications.
The authors call for a pilot program to test AMUS in a few transplant centers before nationwide implementation. They also recommend ongoing monitoring to ensure the score remains accurate as medical practices evolve. If adopted, the new system could reshape the national organ‑allocation policy and set a precedent for other transplant types.
Frequently Asked Questions
The potential benefits are clear: faster access for the most vulnerable patients, fewer deaths on the waiting list, and a more equitable process. However, stakeholders will need to weigh the logistical challenges of updating software, training staff, and aligning with existing regulations.
Q: Could AMUS lead to fewer transplants overall? A: The model is designed to prioritize those at highest risk, which should increase the number of transplants performed before patients die, potentially improving overall transplant outcomes rather than reducing them.